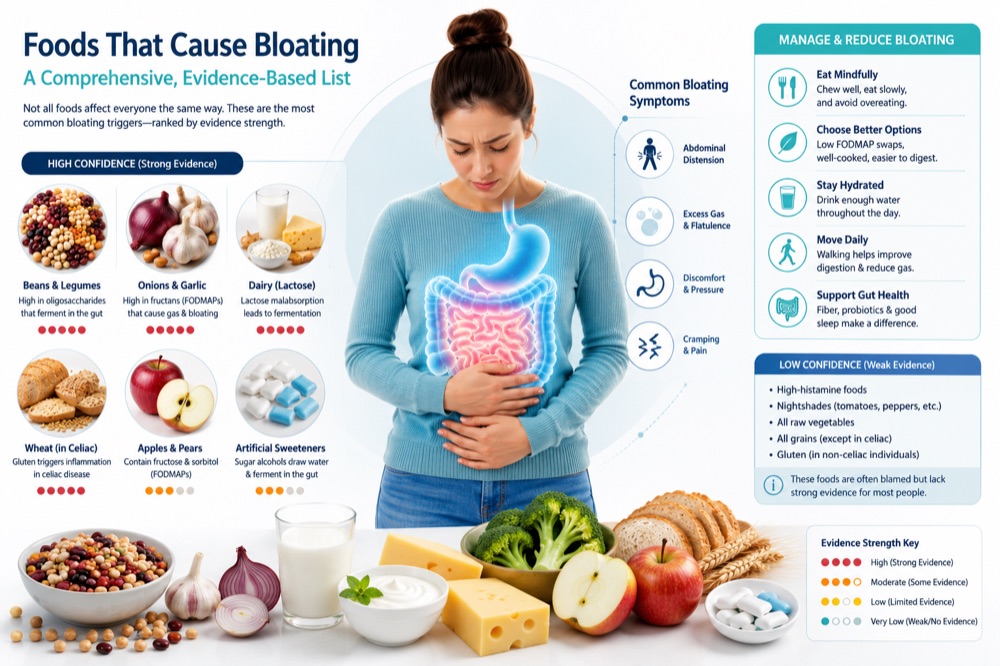
Here’s what most bloating food lists get wrong: they treat all foods as equally problematic for all people. That’s not how food triggers work.
A food that causes severe bloating in someone with IBS may be completely tolerated by someone without gut sensitivity. Lactose causes bloating in the 68% of humans with lactose malabsorption—but not in those who produce adequate lactase.
This guide ranks foods by evidence strength, explains WHY they cause bloating (mechanism matters for finding solutions), and provides practical strategies for managing triggers without spiraling into a 5-food diet.
What you’ll learn:
- High-confidence vs. low-confidence trigger foods
- The mechanism behind each food’s bloating effect
- How to test if YOU’re sensitive to specific foods
- Preparation methods that reduce bloating potential
- When food elimination helps vs. when it harms
The Food Trigger Hierarchy: Not All Foods Are Created Equal
We categorize foods by evidence strength and likelihood of causing bloating.
Table 1: Evidence-Based Food Trigger Hierarchy
| Confidence Level | Foods | Mechanism | % of Population Affected |
|---|---|---|---|
| High Confidence | Beans/legumes, onions, garlic, wheat (in celiac), dairy (in lactose intolerant) | Well-defined mechanisms, reproducible in studies | Variable (15-90% depending on food) |
| Moderate Confidence | Cruciferous vegetables, apples, pears, stone fruits, artificial sweeteners | FODMAP content, osmotic load | 30-50% (higher in IBS) |
| Low Confidence | “High-histamine foods,” nightshades, raw vegetables, gluten (without celiac) | Weak or no evidence for general population | <20% without specific diagnosis |
| Commonly Blamed, Weak Evidence | All grains, all raw foods, all fruits | Overgeneralization, no RCT support | Minimal when tested formally |
Key principle: Start with high-confidence triggers. Don’t eliminate moderate or low-confidence foods without documented personal sensitivity.
High-Confidence Trigger Foods
These foods have strong evidence, reproducible mechanisms, and affect large portions of the population.
Beans and Legumes
Bloating mechanism: Contain raffinose family oligosaccharides (RFOs)—complex sugars humans can’t digest. Gut bacteria ferment them, producing gas.
Bloating potential: ⭐⭐⭐⭐⭐ (Very High)
Specific foods:
- Kidney beans
- Black beans
- Pinto beans
- Chickpeas
- Lentils (moderate)
- Soybeans
Evidence: RCTs show 70-90% of people experience increased gas production after consuming beans
Management strategies:
| Strategy | How It Works | Effectiveness |
|---|---|---|
| Alpha-galactosidase (Beano) | Enzyme breaks down RFOs before bacteria can ferment | High (300-1,200 GalU with first bite) |
| Soaking dried beans | Leaches out some oligosaccharides | Moderate (soak 4+ hours, discard water) |
| Canned beans | Already soaked/processed, lower RFO content | Moderate (rinse thoroughly) |
| Start small, increase gradually | Allows microbiome adaptation | Moderate (start with 2 Tbsp, increase weekly) |
| Lentils instead of beans | Lower RFO content | Moderate (red lentils best tolerated) |
Who should avoid: People with documented sensitivity despite enzyme use
Onions and Garlic
Bloating mechanism: High in fructans (a FODMAP)—fermentable carbohydrates that draw water into the intestine and are rapidly fermented by bacteria.
Bloating potential: ⭐⭐⭐⭐⭐ (Very High for IBS patients)
Evidence: In low-FODMAP RCTs, onions and garlic are among the most commonly identified triggers
Fructan content by food:
| Food | Fructan Content (g/100g) |
|---|---|
| Garlic (fresh) | 17.4 |
| Onion (fresh) | 6.9 |
| Shallots | 7.5 |
| Leek (white part) | 5.0 |
| Asparagus | 2.3 |
| Brussels sprouts | 1.7 |
Management strategies:
| Strategy | How It Works | Effectiveness |
|---|---|---|
| Eliminate for 2-4 weeks, then challenge | Confirms individual sensitivity | High |
| Use onion/garlic-infused oil | Fructans are water-soluble, not oil-soluble | High (flavor without FODMAPs) |
| Use green onion tops or chives | Low in fructans compared to bulb | High |
| Use asafoetida (hing) spice | Traditional substitute, similar flavor | Moderate |
| Small amounts with other foods | Dilution effect may help | Moderate |
Who should avoid: IBS patients (especially IBS-D), those with documented fructan sensitivity
Dairy Products (in Lactose Intolerant Individuals)
Bloating mechanism: Lactose requires lactase enzyme for digestion. When lactase is deficient, undigested lactose is fermented by colonic bacteria.
Bloating potential: ⭐⭐⭐⭐⭐ (Very High in lactose intolerant)
Who’s affected:
- East Asian: 90%+ lactose malabsorption
- African American: 75-80%
- Mediterranean: 50-60%
- Northern European: 15-20%
Lactose content by dairy food:
| Food | Lactose Content (g/serving) | Typical Tolerance |
|---|---|---|
| Ice cream | 6-12 g/cup | Poor |
| Milk (cow’s) | 12-13 g/cup | Poor (if intolerant) |
| Soft cheese (ricotta, cottage) | 3-4 g/serving | Variable |
| Yogurt (with live cultures) | 4-5 g/cup | Often tolerated (bacteria provide lactase) |
| Hard cheese (cheddar, Swiss) | <1 g/serving | Usually tolerated |
| Lactose-free milk | 0 g/cup | Excellent |
Management strategies:
| Strategy | How It Works | Effectiveness |
|---|---|---|
| Lactase enzyme supplementation | Provides enzyme to digest lactose | High (3,000-9,000 FCC units with dairy) |
| Choose lactose-free products | Lactose removed or pre-digested | High |
| Hard cheeses over soft | Lower lactose content | High |
| Yogurt with live cultures | Bacterial lactase helps digestion | Moderate-High |
| Small amounts with meals | Slower transit allows better digestion | Moderate |
Who should avoid: Confirmed lactose intolerant individuals (breath test or elimination-challenge)
Wheat Products (in Celiac Disease or Non-Celiac Sensitivity)
Bloating mechanism:
- Celiac disease: Autoimmune reaction to gluten causes intestinal inflammation
- Non-celiac wheat sensitivity: May be fructans (FODMAP) rather than gluten
Bloating potential: ⭐⭐⭐⭐⭐ (Very High in celiac, Variable in NCGS)
Important distinction:
- Celiac disease (1% of population): Autoimmune, requires strict lifelong gluten avoidance
- Wheat allergy: IgE-mediated, can be severe
- Non-celiac gluten/wheat sensitivity: Diagnosis of exclusion, no biomarker
Foods containing wheat/gluten:
- Bread, pasta, cereals
- Baked goods (cookies, cakes, pastries)
- Beer, malt beverages
- Soy sauce (most brands)
- Seitan (wheat gluten)
- Many processed foods (as filler or thickener)
Management:
- Celiac disease: Strict gluten-free diet (medical necessity)
- Non-celiac sensitivity: Trial elimination, structured reintroduction to determine threshold
Warning: Get celiac testing BEFORE eliminating gluten. Testing requires ongoing gluten consumption.
Moderate-Confidence Trigger Foods
These foods commonly trigger bloating but affect a smaller portion of the population or have more variable effects.
Cruciferous Vegetables
Bloating mechanism: Contain raffinose (like beans) plus sulfur compounds that produce gas during fermentation.
Bloating potential: ⭐⭐⭐⭐ (High, but dose-dependent)
Specific foods:
- Broccoli
- Cauliflower
- Cabbage
- Brussels sprouts
- Kale (moderate)
- Bok choy
Management strategies:
| Strategy | How It Works | Effectiveness |
|---|---|---|
| Cook thoroughly | Breaks down some complex fibers | Moderate |
| Small portions | Stay below individual threshold | High |
| Alpha-galactosidase | Helps break down raffinose | Moderate |
| Choose lower-FODMAP options | Zucchini, carrots, green beans instead | High |
| Fermented (sauerkraut, kimchi) | Pre-digestion by fermentation bacteria | Variable (may help or worsen) |
Who should limit: IBS patients, those with documented sensitivity
High-Fructose Fruits
Bloating mechanism: Excess fructose (more fructose than glucose) is poorly absorbed and fermented by colonic bacteria.
Bloating potential: ⭐⭐⭐⭐ (High in fructose malabsorbers)
Who’s affected: ~30% of population has some fructose malabsorption
High-fructose fruits to limit:
| Fruit | Fructose Content | Fructose:Glucose Ratio |
|---|---|---|
| Apples | High | 2:1 (excess fructose) |
| Pears | High | 2.5:1 |
| Mango | Moderate-High | 1.5:1 |
| Watermelon | Moderate-High | 2:1 |
| Dried fruits (raisins, dates) | Very High | Variable |
Better-tolerated fruits (for most):
- Bananas (not overripe)
- Blueberries
- Strawberries
- Raspberries
- Cantaloupe
- Oranges
- Grapes
Management:
- Limit to <25g fructose per sitting
- Consume with glucose-containing foods (improves absorption)
- Avoid high-fructose corn syrup
Artificial Sweeteners (Polyols)
Bloating mechanism: Sugar alcohols (sorbitol, mannitol, xylitol) are poorly absorbed and osmotically active—draw water into the intestine.
Bloating potential: ⭐⭐⭐⭐ (High, often worse than other FODMAPs)
Common sources:
| Sweetener | Found In | Bloating Risk |
|---|---|---|
| Sorbitol | Sugar-free gum, diet foods, some fruits | High |
| Mannitol | Sugar-free products, mushrooms, cauliflower | High |
| Xylitol | Gum, mints, “natural” sweeteners | Moderate-High |
| Maltitol | Sugar-free candy, protein bars | High |
| Erythritol | Some “keto” products | Lower (better absorbed) |
Management:
- Check ingredient lists on “sugar-free” products
- Limit or avoid if sensitive
- Note: Naturally occurs in stone fruits (peaches, plums, apricots)
Carbonated Beverages
Bloating mechanism: Introduces CO2 gas directly into the stomach—mechanical distension, not fermentation.
Bloating potential: ⭐⭐⭐⭐ (High for gas-related bloating)
Specific beverages:
- Soda (regular and diet)
- Sparkling water
- Beer
- Champagne
- Seltzer
Management:
- Eliminate for 2 weeks, assess improvement
- If sensitive, avoid or limit to small amounts
- Note: “Natural flavors” in sparkling water may also trigger IBS
Low-Confidence Trigger Foods (Commonly Blamed, Weak Evidence)
These foods are frequently blamed for bloating but lack strong evidence in the general population.
Gluten (Without Celiac Disease)
The reality: Studies show many people who self-identify as “gluten sensitive” actually react to fructans (FODMAP) in wheat, not gluten itself.
Evidence: In blinded challenges, most self-reported NCGS patients couldn’t distinguish gluten from placebo
Who should avoid:
- Confirmed celiac disease (testing required)
- Wheat allergy (IgE testing)
- Those with documented non-celiac sensitivity on formal challenge
Who probably doesn’t need to avoid:
- General population without specific diagnosis
- Those who tolerate wheat products without symptoms
Nightshades (Tomatoes, Potatoes, Eggplant, Peppers)
The claim: Nightshades contain alkaloids that cause inflammation and bloating.
The evidence: No RCT evidence supports nightshade avoidance for IBS or functional bloating in the general population.
Who might be sensitive:
- Some individuals with IBD report symptom improvement (anecdotal)
- Those with documented personal sensitivity on challenge
Recommendation: Don’t eliminate without documented personal sensitivity. These foods provide valuable nutrients.
Raw Vegetables
The claim: Raw vegetables are harder to digest than cooked.
The evidence: Limited. Some people report better tolerance of cooked vegetables, but this isn’t universal.
Why some prefer cooked:
- Heat breaks down some fibers (may reduce fermentation)
- Softer texture (may reduce swallowing air)
- Personal preference
Recommendation: If you tolerate raw vegetables without symptoms, no need to avoid. If you notice bloating, try cooking and compare.
“High-Histamine Foods”
The claim: Histamine in foods causes bloating, headaches, and various symptoms.
The evidence: Histamine intolerance is poorly defined with no validated diagnostic criteria. Limited RCT evidence.
Foods often listed:
- Aged cheeses
- Fermented foods
- Wine
- Processed meats
Recommendation: Not recommended for routine elimination. Consider only if classic symptoms (flushing, headaches, hives) accompany GI symptoms—and even then, evidence is weak.
The Over-Restriction Problem
We’ve seen patients arrive with diets restricted to:
- White rice
- Chicken breast
- Water
Still bloated. Still symptomatic.
Why over-restriction backfires:
-
Microbiome narrowing: Less diverse diet → less diverse microbiome → potentially worse symptoms
-
Nutrient deficiencies: Restricting entire food groups risks deficiencies (calcium, fiber, B vitamins)
-
Disordered eating patterns: Food anxiety, social isolation, orthorexia risk
-
Missing the real problem: If bloating stems from motility or muscle coordination issues, dietary restriction treats the symptom while the underlying problem persists
Our threshold for concern: If you’re restricting >5 food groups without confirmed triggers, seek professional guidance.
The Elimination-Challenge Protocol: How to Test YOUR Triggers
Don’t guess. Test systematically.
Phase 1: Elimination (2-4 Weeks)
Steps:
- Choose ONE category to eliminate (not multiple at once)
- Read labels carefully
- Track symptoms daily
- Wait for baseline improvement
Example: Eliminating dairy
- Remove all lactose-containing products
- Track bloating severity (0-10 scale) daily
- Expect improvement within 1-2 weeks if lactose is a trigger
Phase 2: Reintroduction/Challenge (3-7 Days Per Food)
Steps:
- Choose one food to challenge
- Day 1: Small portion (e.g., 1/4 cup milk)
- Track symptoms for 72 hours
- Day 2-3: If no reaction, increase to normal portion
- Day 4-7: Return to baseline before next challenge
Interpretation:
- Clear reaction 2/3 times = Confirmed trigger
- No reaction = Food is tolerated
- Unclear = Repeat challenge or move on
Phase 3: Personalization (Ongoing)
Goal: Maximally varied diet with symptom control
Steps:
- Reintroduce all tolerated foods
- Maintain restriction only of confirmed triggers
- Test threshold: How much can you tolerate?
- Periodic re-testing: Tolerances can change
Food Preparation Methods That Reduce Bloating Potential
How you prepare food matters as much as what you eat.
Table 2: Preparation Strategies
| Food | Preparation Method | Why It Helps |
|---|---|---|
| Beans | Soak 4+ hours, discard water, cook thoroughly | Leaches out oligosaccharides |
| Beans | Use canned, rinse well | Already processed, lower RFOs |
| Vegetables | Cook thoroughly vs. raw | Breaks down some fibers |
| Vegetables | Peel skin | Reduces insoluble fiber |
| Grains | Soak or ferment (sourdough) | Reduces phytates, some FODMAPs |
| Dairy | Choose aged/hard cheeses | Lower lactose content |
| Dairy | Choose yogurt with live cultures | Bacterial lactase helps digestion |
FAQs
Do I need to avoid all high-FODMAP foods forever?
No. The low-FODMAP diet is diagnostic, not a lifelong restriction. After identifying your specific triggers, you reintroduce tolerated foods. Most people can eat a varied diet with only 1-3 confirmed triggers.
Can food intolerances develop later in life?
Yes. Lactose intolerance commonly develops in adulthood as lactase production naturally declines. Some people also develop fructose malabsorption later in life.
Should I get food sensitivity testing before eliminating foods?
No. IgG testing and similar tests are not validated. The elimination-challenge protocol is the gold standard. Save your money.
What if I can’t find any food triggers?
Approximately 40-50% of IBS patients don’t have clear food triggers. This doesn’t mean your symptoms aren’t real—it means food isn’t the primary driver. Consider other interventions (stress management, gut-directed CBT, medications).
Are organic foods less likely to cause bloating?
No evidence. Pesticide residue concerns are separate from bloating mechanisms. The FODMAP content, fiber, and fermentation potential are the same in organic and conventional produce.
Sources
- Eswaran S, et al. The effect of a low FODMAP diet on irritable bowel syndrome symptoms. Gastroenterology. 2024;166(4):609-620.
- Ford AC, et al. American College of Gastroenterology monograph on the management of irritable bowel syndrome. Am J Gastroenterol. 2024;119(S1):S2-S31.
- Vasant DH, et al. British Society of Gastroenterology guidelines for the management of irritable bowel syndrome. Gut. 2024;73(7):1027-1058.
- Chey WD, et al. ACG Clinical Guideline: Management of Celiac Disease. Am J Gastroenterol. 2024;119(2):203-222.
- Moayyedi P, et al. The effect of dietary intervention on irritable bowel syndrome: a systematic review. Am J Gastroenterol. 2024;119(6):1055-1065.
- Black CJ, Ford AC. Global burden of irritable bowel syndrome: trends, predictions, and risk factors. Nat Rev Gastroenterol Hepatol. 2024;21(5):323-336.
- Lacy BE, et al. Rome Foundation Updated Guidelines for Functional Gastrointestinal Disorders. Gastroenterology. 2024;166(1):38-57.
- Camilleri M. Functional gastrointestinal disorders: advances in understanding and management. Lancet. 2024;403(10425):368-382.
- Mayer EA. Gut Feelings: The Connection Between the Brain and the Digestive System. Penguin Random House. 2024.
- Monash University. The Monash FODMAP Diet. 2024. https://www.monashfodmap.com/
- NIH. Lactose Intolerance. 2024.
- NICE. Irritable bowel syndrome in adults: diagnosis and management. 2024.
- Sperber AD, et al. World Gastroenterology Organisation global guidelines: irritable bowel syndrome. J Clin Gastroenterol. 2024;58(2):107-126.
- Kuo B, et al. Update on the diagnosis and management of chronic constipation. Gastroenterol Hepatol. 2024;20(3):145-156.
- Stanghellini V, et al. Gastroparesis: quality of life and health care utilization. Gut. 2024;73(2):215-223.